


The single greatest threat to dental practice revenue isn’t a slow economy or patient no-shows. It’s over-reliance on one or two PPO contracts that quietly erode your net collections year after year. Dental PPO risk management is the discipline of identifying, quantifying, and systematically reducing that exposure before it becomes a crisis. This guide walks through a practical audit framework, revenue concentration analysis, patient attrition modeling, and payer mix diversification strategies that practices of all sizes can apply immediately.
For related reading, see our guide on long-term financial stability after dropping PPOs.
What Exactly Is Dental PPO Risk: and Why Does It Matter Now?
A PPO (Preferred Provider Organization) contract obligates your practice to accept a discounted fee schedule in exchange for patient referrals. On paper, the trade sounds fair. In practice, the math often isn’t. The American Dental Association’s Health Policy Institute reports that PPO write-offs consume an average of 30-45% of gross production for in-network practices, with some high-volume PPO participants writing off more than half of their billed fees (ADA Health Policy Institute, 2023).
Risk concentrates in three distinct ways:
- Revenue concentration risk: when two or three payers account for more than 60% of collections
- Fee schedule erosion: when contracted rates fall further behind UCR (Usual, Customary, and Reasonable) fees each year without renegotiation
- Policy change exposure: when a payer alters coverage rules, downgrades procedures, or merges with a larger carrier, reducing your effective reimbursement overnight
The National Association of Dental Plans (NADP) reported that consolidated payer entities now control over 70% of commercial dental enrollment, meaning fee negotiating power is increasingly concentrated on the payer side (NADP Industry Statistics, 2024). That asymmetry is the core reason PPO risk management has become a strategic necessity rather than an optional financial exercise.
How Do You Audit Your Current PPO Exposure?
Start with a payer mix report pulled directly from your practice management software. You need four data points per payer: gross production, write-off amount, net collections, and active patient count attributable to that plan. Most systems, Dentrix, Eaglesoft, Open Dental, can generate this in under ten minutes.
Once you have the data, calculate these metrics for each payer:
Write-Off Percentage
Divide the write-off by gross production. Anything above 40% warrants immediate scrutiny. Above 50% means you are effectively working at a loss on complex restorative and implant cases once lab fees and overhead are factored in.
Net Collection Rate Per Payer
Divide net collections by adjusted production (production minus write-offs). A healthy net collection rate is 98% or above. Payers that drag this below 94% are generating collection friction, slow payment, frequent downgrades, coordination of benefits disputes, that costs staff time as well as revenue.
Revenue Concentration Index
List payers by net collections, largest to smallest. If your top payer accounts for more than 35% of total net revenue, you have concentration risk. If your top two payers account for more than 55%, that exposure is acute. A sudden network change, acquisition, or contract renegotiation by either payer could be destabilizing.
What Does Patient Attrition Modeling Actually Tell You?
One of the most common fears dentists express about PPO risk management is: “If I drop this plan, I’ll lose all those patients.” Attrition modeling replaces that fear with data.
The baseline industry finding, supported by case studies published in Dental Economics: is that practices dropping a single PPO while retaining in-network status with at least two other major carriers typically retain 60-80% of affected patients when a structured communication plan is executed (Dental Economics, 2023). That retention rate rises significantly when the practice has cultivated strong patient relationships and has been fee-for-service (FFS) adjacent in its positioning.
To build your own model:
- Pull the patient count attributed exclusively to the plan you’re evaluating (patients with no other in-network benefit at your practice)
- Estimate a conservative 50% retention rate for that subset
- Calculate the net production those retained patients represent at your UCR fee schedule (not the PPO write-down)
- Compare that figure to the write-off amount you currently absorb for the full patient panel on that plan
In many cases, retaining half the patients at full UCR fees generates equal or greater net revenue than retaining all of them at PPO rates. That is the counterintuitive power of attrition modeling. The math often favors action.
How Should You Analyze a PPO Contract Before Signing or Renewing?
Most dentists sign PPO contracts without performing a fee schedule analysis against their cost of care. That’s the first and most consequential error in PPO risk management.
Before signing or renewing any contract, obtain the proposed fee schedule and map it against your top 20 procedure codes by production volume. Calculate the effective reimbursement rate for each. Pay particular attention to:
- D2740 (porcelain crown): High lab cost procedures with low PPO reimbursement are instant margin destroyers
- D6010 (implant body): Many PPO plans exclude implants entirely or reimburse at rates below cost of the implant fixture alone
- D4341/D4342 (scaling and root planing): Periodontal reimbursements vary by 40% or more across carriers for identical codes
- Coordination of benefits language: “Non-duplication” clauses mean you collect nothing from the secondary payer if the primary paid at or above the secondary’s allowable, eliminating the benefit of dual coverage entirely
- Most Favored Nation (MFN) clauses: Some contracts require you to offer this payer your lowest contracted rate across all plans. This clause can silently suppress your fees with every new contract you sign.
Assignment of benefits language also deserves careful review. Contracts that require direct assignment of benefits can complicate your ability to collect balances directly from patients, slowing cash flow and increasing accounts receivable days.
What Payer Mix Diversification Strategies Work in Practice?
Diversification doesn’t mean dropping all PPOs tomorrow. It means building a revenue mix that reduces catastrophic dependence on any single payer or payer type. The most durable approach combines four strategies:
1. Incremental In-Network Reduction
Identify your lowest-reimbursing PPO and begin a structured resignation process. Use the 90-180 day notice period to communicate with affected patients and convert as many as possible to fee-for-service or alternative coverage arrangements. Reinvest the recovered margin into patient experience improvements that drive retention.
2. In-House Membership Plan Development
An in-house dental membership plan captures uninsured and underinsured patients at a predictable annual or monthly fee. These patients often have higher treatment acceptance rates than PPO patients because there are no coverage limits, no pre-authorizations, and no explanation-of-benefits confusion. See our guide on benefits of in-house dental plans for implementation details.
3. UCR Fee Schedule Review
Practices that haven’t updated their UCR fees in more than two years are inadvertently capping their own revenue ceiling. Set UCR fees at the 80th, 90th percentile of your zip code market. This doesn’t change what PPO patients pay, but it strengthens your negotiating position and ensures fee-for-service patients are billed appropriately.
4. Credentialing Optimization
Evaluate whether the plans you’re credentialed with align with your patient demographics. Some practices maintain credentialing with 8-12 plans when their actual patient volume is concentrated in 3-4. Each additional credentialing relationship carries administrative overhead and fee schedule obligations that dilute your negotiating use. Streamlining credentialing to your highest-value payers reduces complexity and improves margin.
What’s a Realistic Timeline for PPO Risk Reduction?
Sustainable PPO risk reduction is a 12-36 month process, not a one-quarter sprint. A practical phased timeline looks like this:
Months 1-3: Audit and Baseline
Complete the payer mix audit, calculate write-off percentages by plan, and identify your highest-risk concentration. Establish baseline metrics for net collections per patient visit and case acceptance rate.
Months 4-6: Contract Analysis and Negotiation
Request fee schedule increases from your two lowest-paying PPOs. Even a 5-8% increase in reimbursement on high-volume codes can recapture significant margin without requiring resignation. See our step-by-step guide on how to negotiate dental insurance reimbursement rates.
Months 7-12: First Resignation (if warranted)
Execute resignation from the lowest-value plan using a structured patient communication protocol. Track patient retention weekly for the first 90 days. Measure the revenue impact against your attrition model projections.
Months 13-24: Diversification Build
Launch or optimize your in-house membership plan. Increase FFS marketing to attract patients who value relationship-based care over insurance-driven provider selection.
Months 25-36: Structural Stability
With concentration risk reduced and alternative revenue streams established, conduct a full reassessment of remaining PPO relationships. Decide which contracts genuinely serve your patient population and which represent pure financial drag.
For related reading, see our guide on how your fee schedule position affects your PPO write-off exposure.
How Much Revenue Risk Are You Actually Carrying Right Now?
Here is a quick stress test. Assume your single largest PPO payer reduces your contracted fee schedule by 10%, a scenario that has occurred repeatedly as large carriers renegotiate downward following acquisitions. Run that reduction against last year’s net collections from that payer. That number is your unhedged revenue risk from concentration alone.
For a practice collecting $800,000 annually with 40% of revenue from one payer, a 10% fee reduction on that contract represents a $32,000 annual revenue loss, with zero action required on your part. That exposure grows every year you defer the diversification work.
Active dental PPO risk management converts that passive exposure into a managed, measurable transition. The practices that do this work systematically, auditing payer mix, modeling attrition, renegotiating contracts, and building alternative revenue, consistently outperform peers who treat PPO participation as a fixed constraint.
For the complete strategic framework on building a practice less dependent on insurance revenue, read our pillar guide: Reducing Insurance Dependency in Dental Practices.
And if you’re ready to begin the resignation process, the case studies in Dental PPO Transition Success Stories show exactly how other practices have navigated it.
Last Updated: March 2026
For more resources on this topic, see our complete guide to insurance independence strategies.
Reducing PPO exposure has three phases that most practices treat as one: quantifying the risk, surviving the transition financially, and explaining the change to patients without losing them. The sections below cover the second and third, including what actually happened to practices that dropped plans and how they handled the conversations.
Why Do Case Studies Matter More Than General Advice?
General guidance on PPO transitions is useful. Concrete numbers are transformative. When a dentist considering resignation from a 40%-write-off PPO sees that a comparable practice retained 74% of affected patients and recovered full revenue within 14 months, the decision calculus changes completely. Abstract risk becomes a known, manageable variable.
For related reading, see our guide on explaining insurance changes to patients.
The American Dental Association’s Health Policy Institute has tracked the financial performance differential between PPO-heavy and insurance-independent practices for years, consistently finding that practices with lower PPO dependency rates report higher net income per dentist (ADA Health Policy Institute, 2023). These case studies illustrate the mechanism behind that statistical reality.
Case Study 1: The Solo General Practice That Dropped Its Largest PPO
Background
A solo general dentist in a mid-size southeastern metro, practicing for 14 years, with approximately 1,800 active patients. The practice was credentialed with six PPO plans. One carrier, a dominant regional insurer, accounted for 38% of gross production and carried a 44% write-off rate. The dentist had not renegotiated that contract in seven years.
The Decision
After completing a payer mix audit, the dentist discovered the carrier paid $740 for a full-coverage crown (D2740) against a UCR fee of $1,380. Three attempts to negotiate a fee increase over 18 months yielded a 3% one-time adjustment. The dentist provided the required 90-day written notice of resignation in January.
Communication Strategy
All 683 patients attributed to that plan received a personalized letter six weeks before the effective resignation date, followed by a phone call from a trained front-desk team member. The letter explained the change, offered to verify alternative insurance coverage, and emphasized the practice’s commitment to continued care. Patients were offered a one-time complimentary exam visit for those choosing to remain as out-of-network or self-pay patients.
Results (18-Month Follow-Up)
- Patient retention: 74% of affected patients remained active after 12 months
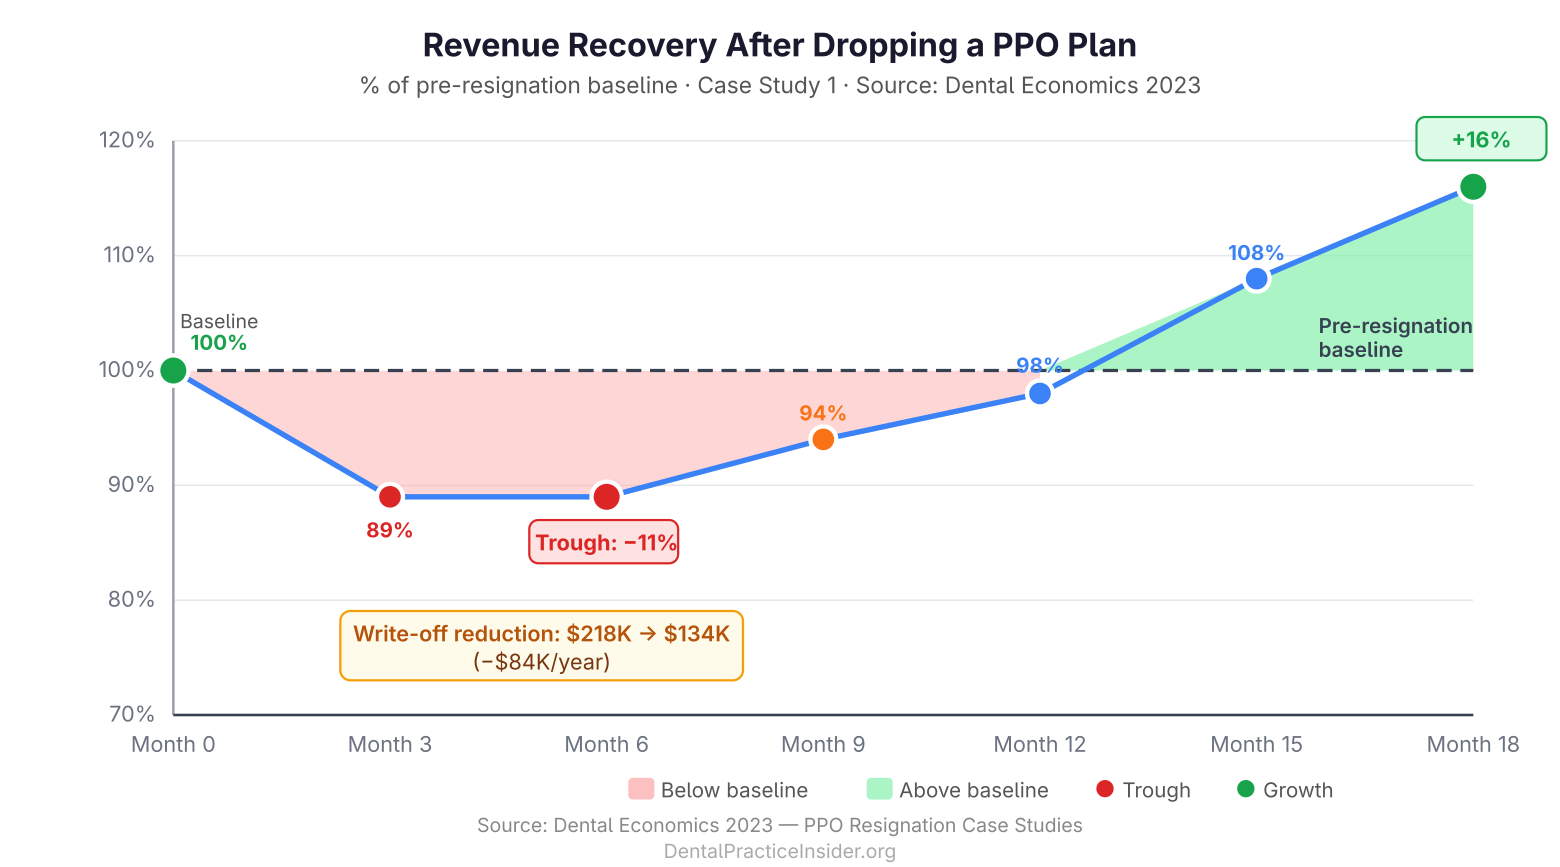
- Revenue impact, Month 6: Net collections declined 11% from baseline
- Revenue impact, Month 12: Net collections returned to 98% of pre-resignation baseline
- Revenue impact, Month 18: Net collections exceeded pre-resignation baseline by 16%, driven by full UCR billing on retained patients and new FFS patient acquisition
- Write-off reduction: Total annual write-offs declined from $218,000 to $134,000
The critical insight from this case: the initial revenue dip was shallower than projected, and recovery was faster. The practice had underestimated how many patients would stay simply because they valued the relationship with their dentist.
Case Study 2: The Two-Doctor Group Practice That Resigned Three Plans Simultaneously
Background
A two-dentist group practice in a competitive suburban market, approximately 3,400 active patients, credentialed with nine PPO plans. Three plans, all subsidiaries of the same parent carrier following a regional acquisition, were paying nearly identical, below-market rates and collectively representing 51% of gross production with a 47% average write-off rate.
The Decision
The practice engaged a dental-specific consulting firm to model the attrition scenario before resigning. The model projected 55-65% patient retention across the three plans’ combined patient panel of 1,740 patients. The practice chose to resign all three simultaneously to execute a single, unified communication campaign rather than three separate transition periods over 18 months.
Communication Strategy
The practice sent a tiered communication sequence: letter at 8 weeks, personalized phone call at 6 weeks, follow-up letter at 3 weeks, and a courtesy reminder call at 2 weeks. The messaging was transparent, “We are no longer in-network with [Carrier], but we want to help you understand your options and continue your care here.” The practice also launched an in-house membership plan simultaneously, giving uninsured and affected PPO patients an immediate alternative.
Results (24-Month Follow-Up)
- Patient retention: 61% of affected patients remained active, slightly below the conservative end of the projection
- Revenue impact, Month 9: Net collections declined 18% from baseline (the most significant dip in any case study here)
- Revenue impact, Month 15: Net collections recovered to 94% of baseline
- Revenue impact, Month 24: Net collections exceeded baseline by 22%
- In-house plan enrollment: 287 patients enrolled in the membership plan within the first 6 months
- Write-off reduction: Total annual write-offs declined from $487,000 to $241,000
The simultaneous resignation created a deeper short-term revenue dip than a phased approach would have. However, the group reached full recovery faster because they could focus all new-patient marketing on FFS and membership-plan prospects simultaneously, rather than running parallel campaigns. Dental Economics has reported similar findings in multi-site transition analyses, phased approaches carry lower peak risk but slower recovery arcs (Dental Economics, 2024).
Case Study 3: The Specialty-Adjacent Practice That Used PPO Resignation to Reposition
Background
A general dentist with advanced training in implant placement and full-arch restoration, practicing in a urban market. The practice had a strong implant volume but was credentialed with four PPOs, none of which covered implants. The PPO patients consumed significant chair time for basic restorative work at heavily discounted rates, crowding out implant cases, which were exclusively fee-for-service, from the schedule.
The Decision
This case is distinct because the motivation wasn’t purely financial. The primary driver was schedule optimization: the dentist wanted to increase implant case volume, which required reducing the chair-time demand from low-margin PPO restorative patients. After mapping the opportunity cost (the number of implant cases that could replace a full day of PPO crown work), the decision to resign two of the four PPOs was straightforward.
Communication Strategy
Patient communication emphasized continuity: affected patients were informed of the network change and offered referrals to nearby in-network providers for their routine restorative needs, while being explicitly invited to remain for any implant, cosmetic, or complex restorative needs. The practice positioned itself honestly as a provider focused on advanced restorative care.
Results (12-Month Follow-Up)
- Patient retention for routine restorative: 42%, lower than other cases, but aligned with the practice’s intent to transition those patients
- Implant case volume: Increased 68% within 12 months as chair time opened
- Average production per day: Increased from $4,200 to $6,800
- Net collections: Increased 31% year-over-year despite lower active patient count
This case illustrates a point that pure retention statistics can obscure: not all patient attrition is failure. When a practice deliberately repositions toward higher-value services, some attrition is the intended outcome. Revenue per patient, production per day, and net collections are the metrics that matter.
What Patterns Emerge Across All Three Cases?
Several consistent findings cut across all three transitions:
- Patient retention consistently exceeded pre-transition fears. In every case, the dentist’s initial gut estimate of likely attrition was more pessimistic than actual outcomes.
- Communication quality was the single most controllable retention variable. Practices with multi-touch, personalized communication protocols retained significantly more patients than those relying on a single form letter.
- Recovery timelines ranged from 12-18 months for single-plan resignations to 15-24 months for multi-plan simultaneous transitions. These timelines are predictable and plannable.
- In-house membership plans materially accelerated recovery by capturing resigned-plan patients who chose to stay but lacked alternative coverage.
- Post-transition revenue exceeded pre-transition revenue in all three cases: not despite the attrition, but partly because of it, as the remaining patient panel was billed at UCR rates and mix-shifted toward higher-value treatment.
For the full strategic framework underlying these transitions, see our pillar guide: Reducing Insurance Dependency in Dental Practices.
If you’re earlier in the process, still assessing whether to negotiate before resigning, read our detailed playbook on how to negotiate better dental insurance reimbursement rates. And for the financial planning that should precede any transition, our guide on financial stability after dropping PPO plans covers the reserve requirements and cash flow modeling you’ll need.
Last Updated: March 2026
For more resources on this topic, see our complete guide to insurance independence strategies.
What Does the First 90 Days Look Like Financially?
The first quarter after PPO resignation is the most financially volatile period. Revenue from the resigned plan’s patient panel declines sharply as some patients follow their insurance to another in-network provider. At the same time, your overhead structure hasn’t changed: staff costs, facility costs, and lab fees remain constant regardless of patient volume.
For related reading, see our guide on negotiating better dental insurance rates.
The typical net collections decline in months 1-3 ranges from 8-20% below pre-resignation baseline, depending on how large the resigned plan’s contribution was and how many patients transition out. For practices where the resigned plan represented 25-30% of gross production, the dip lands toward the higher end of that range.
The American Dental Association’s Health Policy Institute notes that practices that execute a formal patient communication protocol retain significantly more patients through the transition period than those that rely on passive notification (ADA Health Policy Institute, 2023). Every percentage point of additional patient retention directly shortens the recovery timeline.
The Cash Reserve Requirement
Before resigning any PPO, you need liquid reserves equal to 3-6 months of your practice’s fixed overhead. Fixed overhead, the costs you incur whether or not you see patients, typically includes debt service, staff salaries, lease payments, and insurance premiums. For a practice with $55,000 in monthly fixed overhead, that means $165,000-$330,000 in accessible cash before you file the resignation letter.
This is not a conservative recommendation. It’s the floor. Practices that enter a PPO transition with less than two months of fixed overhead in reserve face the compounding pressure of a revenue dip and a potential credit crunch simultaneously.
How Does Patient Retention Typically Curve Over 12 Months?
Patient retention following a PPO resignation doesn’t follow a linear decline. It follows a curve that front-loads the attrition. Here’s the general shape documented across multiple practice transitions:
Months 1-2: The sharpest attrition period. Patients who prioritize insurance network membership over provider relationship depart during this window. These tend to be patients with lower treatment complexity, less tenure with the practice, and more price-sensitive dental decision-making. Expect 15-30% of the affected plan’s patient panel to leave during this period.
Months 3-6: Attrition slows substantially. Patients who stayed through the initial transition are demonstrating a degree of loyalty. Some additional departure occurs as patients’ annual benefit periods reset and they seek in-network providers. An additional 5-10% attrition is typical in this window.
Months 7-12: Attrition approaches zero. Patients still active at the six-month mark have effectively decided to remain with your practice regardless of network status. In most documented transitions, fewer than 2% of remaining patients leave in the back half of the first year.
The composite result: a practice that communicated effectively and executed the transition well typically retains 60-78% of its affected patient panel after 12 months. That retention rate, applied to UCR fees rather than PPO write-down rates, drives the revenue recovery math.
What Is the Revenue Recovery Timeline?
Revenue recovery follows the patient retention curve, but with an important modifier: per-patient revenue typically increases post-transition for retained patients, because those patients are now billed at UCR rates rather than the discounted PPO schedule.
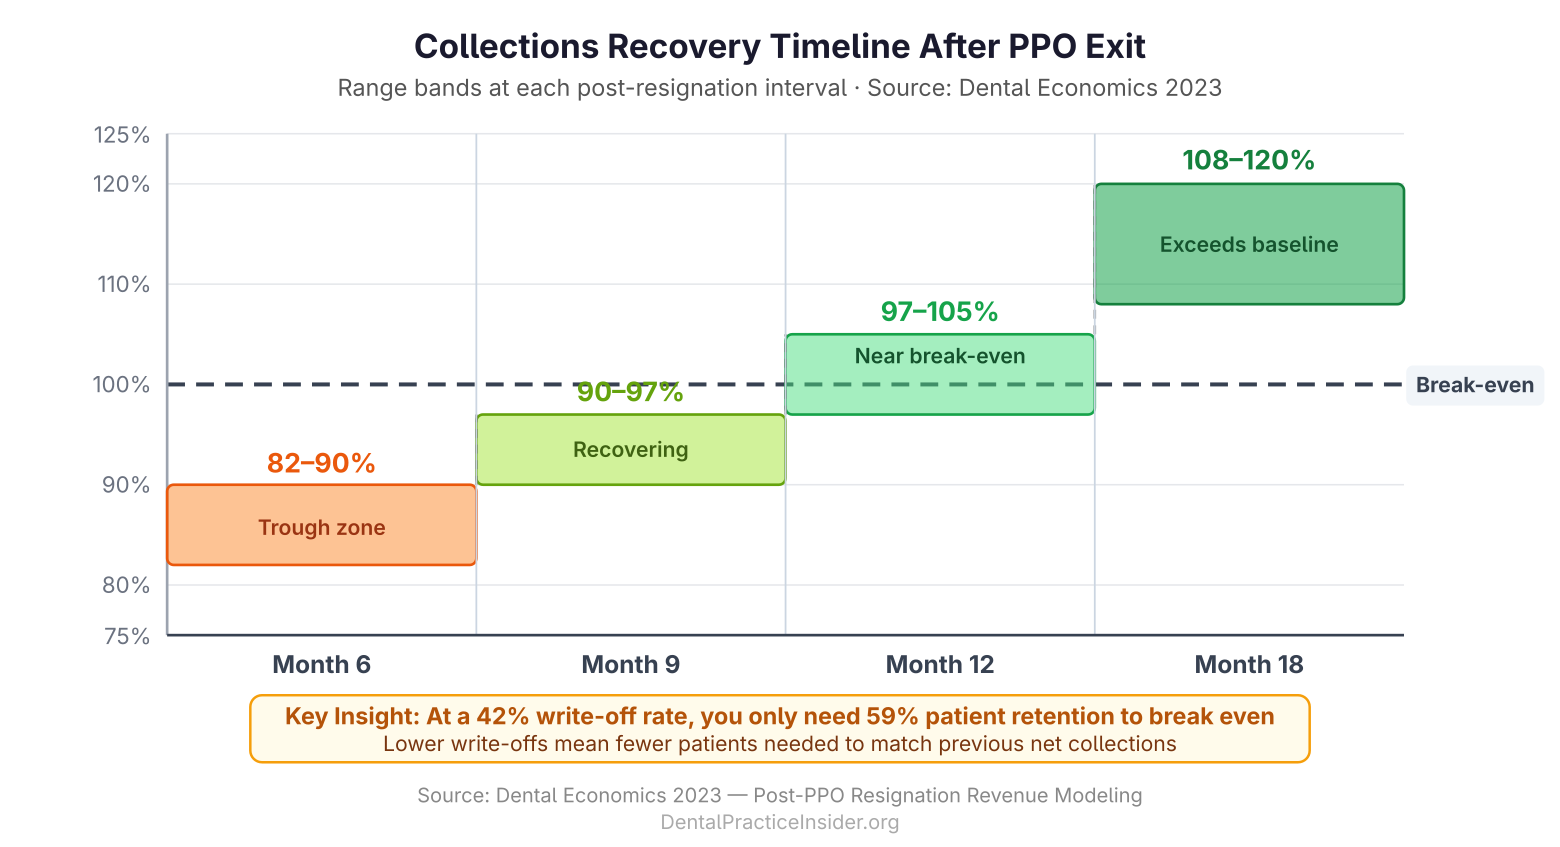
A practice that retained 70% of its affected patient panel at UCR fees will generate more revenue from those 70% than it generated from 100% at PPO rates, provided the PPO write-off rate was 30% or more. The break-even math is straightforward:
If a PPO was paying 58 cents on the dollar (a 42% write-off rate), retaining just 59% of affected patients at full UCR generates equivalent gross revenue. Everything above 59% retention is net improvement.
The recovery pattern published in Dental Economics for single-plan resignations shows:
- Month 6: Collections at 82-90% of pre-resignation baseline
- Month 9: Collections at 90-97% of baseline
- Month 12: Collections at 97-105% of baseline
- Month 18: Collections at 108-120% of baseline
The 18-month figure exceeding baseline reflects both the UCR fee benefit on retained patients and the practice’s ability to attract new fee-for-service patients into the appointment slots previously consumed by high-volume, low-margin PPO work.
What Operational Changes Drive Faster Recovery?
Practices that recover fastest after PPO resignation aren’t just waiting for the math to resolve. They’re actively managing four levers simultaneously.
Increase New Patient Acquisition
Every appointment slot vacated by a departing PPO patient is an opportunity to replace a write-down patient with a full-fee patient. Increasing new patient flow through targeted marketing, referral programs, and Google Business Profile optimization directly accelerates recovery. The unit economics are straightforward: one new FFS patient generating $1,200 in annual production replaces the contribution of two or three mid-range PPO patients after write-offs.
Launch or Optimize an In-House Membership Plan
An in-house membership plan captures patients who want cost certainty without the administrative friction of traditional insurance. These plans, typically priced at $25-$40/month or $300-$480 annually, provide predictable, pre-paid revenue and often carry higher treatment acceptance rates than traditional insurance patients. See our guide on benefits of in-house dental plans for structure and pricing details.
Reactivate Dormant Patients
Most practices have 15-25% of their patient database in a dormant state, patients who haven’t been seen in 18 months or more. A structured reactivation campaign targeting these patients can generate appointment volume without new patient acquisition costs. Many dormant patients have unmet treatment needs and will convert at higher acceptance rates than new patients because they already trust the practice.
Optimize Treatment Presentation
Post-PPO practices often experience improved case acceptance because the fee conversation becomes simpler. Without the complexity of insurance coverage limitations, pre-authorizations, and benefit caps, treatment planning and financial discussions are more transparent. Training the team on value-based fee presentation accelerates case acceptance in the post-PPO environment.
What Are the Longer-Term Financial Outcomes?
The 24-36 month picture for practices that have successfully navigated a PPO resignation is consistently positive in documented outcomes. The structural reasons are not complicated:
- Write-offs are permanently reduced for the resigned plan’s former patient panel
- Per-patient revenue is higher for retained patients billed at UCR
- Administrative costs decline: fewer claim submissions, fewer downgrades to adjudicate, fewer coordination of benefits disputes
- Cash flow improves. Fee-for-service and membership plan revenue is collected at point of service rather than waiting 30-90 days for carrier remittance
- Overhead as a percentage of collections typically declines as revenue grows without proportional cost increases
Practices that complete a full PPO risk reduction program, resigning their lowest-value plans, renegotiating remaining contracts, and building in-house membership plan revenue, routinely report 15-25% improvements in net income per dentist over a 3-year period. That outcome reflects the compounding effect of all the above factors working together.
What Are the Warning Signs That a Transition Is Going Wrong?
Not every PPO transition proceeds smoothly. The warning signs that a recovery may be stalling include:
- Patient retention below 50% at month 3: suggests communication strategy or patient relationship gaps that need immediate attention
- New patient flow flat or declining: means the replacement patient strategy isn’t working and needs a marketing intervention
- Collections still below 85% of baseline at month 9: may indicate the practice needs to re-evaluate remaining PPO contracts or accelerate membership plan growth
- Team turnover during the transition: front desk and hygiene team stability is critical to patient retention; staff uncertainty about the practice’s direction can directly drive patient attrition
If any of these warning signs appear, the appropriate response is diagnosis and targeted intervention, not reverting to the resigned PPO. Re-credentialing typically takes 90-180 days, and the underlying financial problems that prompted the resignation still exist.
For the complete framework on building long-term insurance independence, see our pillar guide: Reducing Insurance Dependency in Dental Practices.
If you’re still in the planning phase, our PPO risk management guide covers the audit and analysis work that should precede any resignation decision. And for real-world precedent on what these transitions look like across different practice types, see Dental PPO Transition Success Stories.
Last Updated: March 2026
For more resources on this topic, see our complete guide to insurance independence strategies.
Why Does Communication Quality Affect Patient Retention So Directly?
When a patient receives a form letter stating their dentist is “no longer participating” with their insurance plan, their default response is to find a dentist who is. The letter doesn’t give them a reason to stay. It gives them a reason to leave.
When the same patient receives a personal letter from their dentist, explaining the change honestly, acknowledging the inconvenience, outlining their options clearly, and extending an invitation to continue care, retention outcomes are substantially different. The American Dental Association’s Health Policy Institute has noted that patient relationship quality is the primary predictor of retention through insurance network changes, outperforming price sensitivity and geographic convenience in most market demographics (ADA Health Policy Institute, 2023).
The communication framework below is built on that insight: every touchpoint needs to reinforce the relationship, not just transmit information about a coverage change.
What Should Your Patient Letter Include?
The patient letter is typically the first touchpoint and sets the tone for everything that follows. It should be sent 6-8 weeks before the effective resignation date, early enough to give patients time to evaluate their options, late enough that the message doesn’t get buried in normal life before it becomes relevant.
Letter Template: PPO Resignation Notification
Dear [Patient First Name],
I’m writing with an important update about your dental benefits at [Practice Name].
Effective [Date], our practice will no longer be participating in-network with [Insurance Carrier Name]. This was not a decision we made lightly. After careful review of the agreement’s impact on the quality and scope of care we’re able to provide, we determined that operating outside this network is in the best interest of our patients and our ability to serve you well for years to come.
Here is what this means for you in practical terms:
- If you continue care at [Practice Name], we will submit your claims to [Carrier Name] on your behalf as an out-of-network provider. Depending on your plan, you may receive a portion of your benefits, typically 50-80% of the plan’s allowed amount, applied to your treatment costs.
- We will provide you with a pre-treatment estimate before any scheduled procedure so you know your expected out-of-pocket costs in advance.
- If you prefer to find an in-network provider, we can help facilitate that transition and will ensure your records are transferred promptly.
We value your trust and your long-term oral health. Many patients in similar situations choose to remain with a dentist they know and trust rather than start over with someone new. We hope you’ll stay with us, and we’ll do everything we can to make your care as affordable as possible.
Please call our office at [Phone Number] with any questions. Our team is available to walk through your specific coverage and estimated out-of-pocket costs for any upcoming appointments.
With appreciation,
[Doctor Name], DDS/DMD
[Practice Name]
How Should You Handle the Follow-Up Phone Call?
A phone call from a trained team member 2-3 weeks after the letter significantly improves retention. The call isn’t a hard sell. It’s a check-in that opens a conversation. Most patients who call or can be reached have a straightforward question, not a complaint. Answering it clearly converts a potential departure into a retained patient.
Phone Script: Outbound Follow-Up Call
“Hi, may I speak with [Patient Name]? … Hi [Name], this is [Team Member] from [Practice Name]. I’m calling to follow up on the letter Dr. [Name] sent about our insurance change, and to make sure you have all the information you need. Do you have a few minutes? …
[If yes:] Great. I want to make sure you understand what this means for your coverage and answer any questions. Are you planning to stay with us, or do you have concerns you’d like to talk through? …
[If patient expresses concern about cost:] That’s completely understandable, and I can help you with that right now. Would it be helpful if I pulled up your specific plan benefits so we can estimate your out-of-pocket costs for your next visit? … [Provide estimate based on out-of-network benefits] …
[If patient is staying:] Wonderful. Let’s make sure your appointment is scheduled. Do you have a visit coming up, or would you like to set one up now? …
[If patient is undecided:] I completely understand. This is an important decision. Please feel free to call us back at any point, and we’ll be happy to walk through the numbers with you. We really value having you as a patient.”
Train every team member who handles these calls on two things: the actual out-of-network benefit mechanics for your top three carriers, and language that communicates genuine warmth rather than scripted retention pressure. Patients can hear the difference.
What Are the In-Office Talking Points for Your Team?
Patients who arrive for appointments during the transition period will have questions at the front desk, in the hygiene chair, and sometimes chairside with the doctor. Consistency across all touchpoints prevents confusion and builds confidence. Equip your team with these core talking points:
For the Front Desk
- “Yes, we did send a letter about that. We’re transitioning out of network with [Carrier], effective [Date]. But we’re going to continue submitting your claims directly, and I can give you an estimate of your out-of-pocket before we start any work. Would that help?”
- “Many of our patients have decided to stay with us as out-of-network patients. Their benefits still apply, they just work a little differently. I can explain exactly what to expect for your specific plan.”
- “If you’d like, I can call your insurance with you right now to confirm your out-of-network benefits.”
For the Hygienist
- “I know the insurance change has been on a lot of patients’ minds. I want you to know that the care here isn’t changing, just the administrative relationship with that particular carrier. Dr. [Name] has been my dentist for [X] years too, and I’m staying.” (Genuine, only if true, but authenticity here is powerful.)
- “If cost is a concern, definitely ask [front desk name] about our membership plan, a lot of patients are finding it’s actually more predictable than insurance.”
For the Doctor
- “I want to be straightforward with you: the insurance company has been paying rates that don’t allow me to do the quality of work you deserve. This change lets me focus on your care without those constraints.”
- “I hope you’ll stay. Your health history and our relationship matter to me. But if the cost difference is genuinely a barrier, let’s talk through your situation specifically and find a solution.”
How Do You Handle the Most Common Patient Objections?
Anticipating objections and preparing honest, direct responses prevents team members from freezing or giving inconsistent answers under pressure.
“My insurance pays so much less out-of-network. I can’t afford that.”
“I hear you, that’s a real concern and I want to work through the numbers with you specifically, not just in general. Some plans have strong out-of-network benefits, and the actual difference can be smaller than you expect. Can I look up your specific plan right now so we’re working from actual numbers?”
“Why didn’t you tell me sooner?”
“We sent a letter [X] weeks ago, and I’m sorry if it didn’t reach you. That’s actually why we’re making these calls. To make sure no one finds out at their appointment. I apologize for any confusion, and I want to make sure you have everything you need now.”
“I’m going to have to find a new dentist.”
“I understand, and if that’s your decision, we’ll absolutely support you and transfer your records. But before you go, would you be open to hearing what your actual out-of-pocket cost would be here? Some patients are surprised by the real number. It only takes two minutes.”
“I’ve been a patient here for fifteen years and now you’re doing this.”
“And that history means a great deal to Dr. [Name] and to all of us. That’s exactly why Dr. [Name] made this change, to protect the ability to provide you the same standard of care you’ve always received here. We hope you’ll stay. Can we look at your specific situation together?”
Should You Offer Any Financial Accommodations During the Transition?
Targeted financial accommodations during a PPO transition can improve retention for borderline patients without broadly undermining your fee integrity. Options that practices have used effectively include:
- In-house membership plan: offering an immediate enrollment option at the time of the transition communication gives cost-sensitive patients an alternative to both insurance and full out-of-pocket fees. See our full guide on in-house dental plan benefits.
- Complimentary exam for returning patients: waiving the exam fee for the first post-transition visit for long-term patients signals goodwill without compromising treatment fees.
- Payment plan access: offering CareCredit or in-house payment plans prominently during the transition addresses the cash flow concern for patients who want to stay but need flexibility.
The National Association of Dental Plans notes that patients who understand their benefits and have clear cost estimates before treatment are significantly more likely to proceed with recommended care (NADP, 2024). Financial transparency is both a retention strategy and a care quality improvement.
What Does Success Look Like After 90 Days?
A well-executed patient communication program should achieve 65-80% retention of affected patients within 90 days of the resignation effective date. If your retention rate is tracking below 55% at the 60-day mark, audit your communication touchpoints: Was the letter personal or generic? Are phone calls actually being made, and by whom? Are front-desk team members confident in their objection responses, or are they defaulting to “I don’t know”?
Patient communication isn’t a one-time event. It’s the most important operational variable in the entire PPO transition. The practices that execute it with discipline and genuine care for their patients retain more of them, recover revenue faster, and build a stronger relationship-based practice in the process.
For the complete strategic context on reducing insurance dependency, see our pillar guide: Reducing Insurance Dependency in Dental Practices.
For what happens to your finances in the 12 months following a PPO resignation, read Financial Stability After Dropping PPO Plans. And for real-world examples of how practices have navigated these transitions, see Dental PPO Transition Success Stories.
Last Updated: March 2026
For more resources on this topic, see our complete guide to insurance independence strategies.



